




The Disease
An infectious disease
Chikungunya is an infectious disease caused by an arbovirus. “Arthropod-borne viruses” are viruses transmitted by blood-feeding arthropods (notably mosquitoes, sandflies, and ticks). They belong to three main families: the Flaviviridae, the Togaviridae, and the Bunyaviridae." data-tooltip-title="Arboviruses (arthropod-borne viruses) are viruses transmitted by blood-feeding arthropods (notably mosquitoes, sandflies, and ticks). They belong to three main families: the Flaviviridae, the Togaviridae, and the Bunyaviridae." data-tooltip-content="" data-tooltip-placeholder-is-selection="true" data-tooltip-placeholder-is-selection-text="arbovirus" data-tooltip-data="[{"tooltipTitle":"Arboviruses « arthropod-borne viruses » are viruses transmitted by blood-feeding arthropods (mosquitoes, sandflies, and ticks, among others). They belong to 3 main families, the Flaviviridae, the Togaviridae, and the Bunyaviridae.","tooltipContent":"","placeholderIsSelection":"true","placeholderIsSelectionText":"arbovirus"}]">arbovirus: the chikungunya virus. It belongs to the Togaviridae family (genus Alphavirus) and was first isolated in Uganda in 1952 during an epidemic in East Africa. The name “chikungunya” comes from the Makonde language and means “the man who walks bent over.” The disease typically presents with fever and joint pain, which usually resolve spontaneously after a few days
This virus is transmitted from person to person primarily through the bites of mosquitoes of the genus Aedes, mainly Aedes aegypti and Aedes albopictus (also known as the tiger mosquito).
Key Statistics on Chikungunya

Several modes of chikungunya transmission
Vector-borne transmission
The chikungunya virus is primarily transmitted by blood-feeding arthropods (which include insects and mites) that transmit an infectious agent (virus, bacterium, parasite) from one vertebrate to another" data-tooltip-title="blood-feeding arthropods (which include insects and mites) that transmit an infectious agent (viruses, bacteria, parasites) from one vertebrate to another" data-tooltip-content="" data-tooltip-placeholder-is-selection="true" data-tooltip-placeholder-is-selection-text="vectors" data-tooltip-data="[{"tooltipTitle":"arthropod (including insects and mites) hematophagous (feeding on blood) that transmits an infectious agent (virus, bacteria, parasite) from one vertebrate to another","tooltipContent":"","placeholderIsSelection":"true","placeholderIsSelectionText":"vectors"}]">vectors. For this virus, the vectors are mosquitoes of the genus Aedes, primarily Aedes albopictus (also known as the tiger mosquito) and Aedes aegypti.
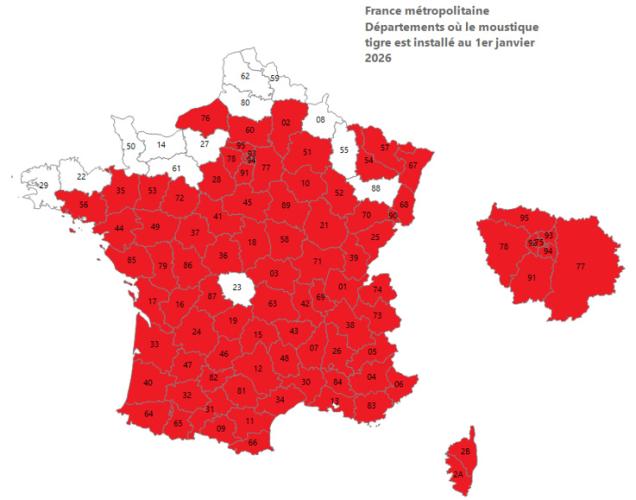
Chikungunya is an infection that is prevalent mainly in tropical and intertropical regions where the vectors Aedes aegypti and Aedes albopictus are present. In France, Aedes aegypti is found in the French West Indies, French Guiana, and Mayotte, while Aedes albopictus is found on the island of Réunion. Aedes albopictus is also found in temperate regions, particularly in Europe. In mainland France, by 2026, it had become established in 83 departments.
These Aedes mosquitoes thrive primarily in urban areas and do not travel far during their lifetimes. Females lay their eggs in breeding sites where standing water is necessary for larval development: rainwater collectors, vases, saucers, used tires, poorly maintained gutters, various types of trash that can hold stagnant water, as well as tree hollows and certain plants that can trap water (bamboo, bromeliads, etc.). Artificial breeding sites—that is, those created by humans—are the primary egg-laying sites for these mosquitoes.
Aedes mosquito bites occur mainly during the day, with peak activity at dawn and dusk. When a mosquito bites an infected person at a time when the virus is present in their blood." data-tooltip-title="when the virus is present in their blood." data-tooltip-content="" data-tooltip-placeholder-is-selection="true" data-tooltip-placeholder-is-selection-text="viremic phase" data-tooltip-data="[{"tooltipTitle":"the time when the virus is present in their blood.","tooltipContent":"","placeholderIsSelection":"true","placeholderIsSelectionText":"viremic phase"}]">viremic phase, the mosquito picks up the virus from this person’s blood. The virus then multiplies within the mosquito for approximately 5 to 7 days, a period known as the extrinsic phase. At the end of this extrinsic phase, the mosquito can transmit the virus and infect another person.
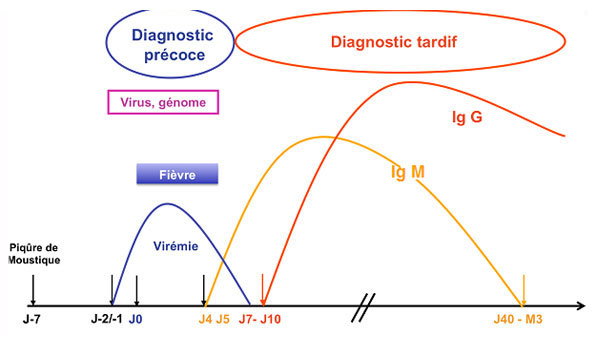
For chikungunya, this refers to the time when the virus is present in the mosquito’s blood." data-tooltip-title="the time when the virus is present in the mosquito’s blood." data-tooltip-content="" data-tooltip-placeholder-is-selection="true" data-tooltip-placeholder-is-selection-text="viremic phase" data-tooltip-data="[{"tooltipTitle":"the time when the virus is present in their blood.","tooltipContent":"","placeholderIsSelection":"true","placeholderIsSelectionText":"viremic phase"}]">The viremic phase begins approximately 1 to 2 days before the onset of clinical signs and lasts up to 7 days after that.
Transmission via products of human origin
During the viremic phase, the virus is present in the blood and certain tissues. Transmission of the Chikungunya virus through products of human origin (blood transfusion, organ or cell transplantation) is considered possible.
Other modes of transmission
A few cases of mother-to-fetus transmission (during the second trimester of pregnancy) and perinatal transmission have been documented
Symptoms and complications
In approximately 10 to 40% of cases, Chikungunya is asymptomatic (the percentage varies depending on the outbreak).
For 60% to 90% of people infected with the virus, symptoms develop after an incubation period averaging 3 to 7 days (ranging from 1 to 12 days). Typical symptoms include:
- A sudden onset of high fever
- Joint pain, which can be severe, primarily affecting the small joints of the extremities (wrists, ankles, fingers)
- Muscle pain
- Headaches
- A maculopapular rash
The course of the illness is usually favorable after about ten days, with no lasting effects. However, chikungunya can progress to a chronic phase characterized by persistent joint pain. This pain can occur in 30 to 40% of patients and last for several months, or even several years in some patients.
Diagnosis
Chikungunya virus infection is diagnosed using direct methods (detection of the virus by culture or of its genome by PCR) or indirect methods (detection of antibodies by serology).
The diagnostic strategy for the chikungunya virus is as follows:
- Up to 5 days after the onset of symptoms (Day 5): RT-PCR
- Between D5 and D7: RT-PCR and serology
- After Day 7: serology only (IgG and IgM) with a second confirmatory sample taken no earlier than 10 days after the first sample
Therefore, it is essential to accurately identify the date of symptom onset in order to select the appropriate tests.
Early testing (up to Day 7) using RT-PCR should be prioritized due to its higher specificity compared to serology. IgM antibodies can be detected as early as the fifth day after the onset of clinical signs and persist for an average of 2 to 3 months. IgG antibodies appear a few days after IgM and persist for life.
The detection of IgM must be followed by a second sample for confirmation, taken at least 10 days after the first. A diagnosis of chikungunya will be confirmed if IgG is detected in the second sample, or if there is a rising IgG titer (generally at least four times higher than in the first blood sample).
Kinetics of the Virus and IgM and IgG Antibodies During Chikungunya Virus Infection
Blood samples can be collected by any clinical laboratory. Each sample must be accompanied by a clinical information form. Laboratory
confirmation of chikungunya is particularly important in the French overseas departments and in mainland France where the vector (Aedes albopictus or Aedes aegypti) is established.
Individual Prevention
Individual prevention relies on avoiding mosquito bites and vaccination.
Prevention of Mosquito Bites
- Eliminating potential larval breeding sites around homes (standing water, gutters, vases, buckets, trash, etc.);
- Wear loose-fitting, covering clothing (long sleeves and pants);
- Use skin repellents in spray or cream form on parts of the body not covered by clothing;
- Install mosquito screens on doors and windows;
- Use a mosquito net when sleeping, even during the day;
- Create airflow (using fans or, if possible, air conditioning).
This protection is especially important during the day. Aedes mosquitoes primarily bite during the day, with peak activity at dawn and dusk.
Vaccination
Two vaccines have received European marketing authorization:
- the IXCHIQ vaccine from Valneva;
- and the VIMKUNYA vaccine from Bavarian Nordic.
In 2026, given the active circulation of the chikungunya virus in Mayotte and French Guiana—with a risk of the situation escalating into an epidemic—the French National Authority for Health (HAS) recommended, in its opinions dated April 9 and 24, 2026, the use of the VIMKUNYA vaccine:
- for people aged 65 and older (with or without comorbidities);
- for people aged 18 to 64 with comorbidities.
The VIMKUNYA vaccine may be offered to other populations, taking into account the documented duration of protection, which is limited to six months, and the lack of data in immunocompromised individuals. It is not recommended for pregnant or breastfeeding women due to a lack of data.
The HAS states that the IXCHIQ vaccine may be offered to people aged 18 to 64 following a thorough review of the potential benefits and risks; it maintains its suspension for people aged 65 and older due to pharmacovigilance signals. The IXCHIQ vaccine is not recommended for pregnant or breastfeeding women and is contraindicated for immunocompromised individuals.
The HCSP has been asked to issue recommendations on chikungunya vaccination for travelers; the 2026 recommendations are currently being developed.
Learn more:
- Opinion No. 2026.0022/AC/SESPEV of April 9, 2026, from the High Authority for Health (HCSP) regarding the IXCHIQ and VIMKUNYA vaccines in the context of the re-emergence of chikungunya in French Guiana
- Opinion No. 2026.0027/AC/SESPEV dated April 24, 2026, issued by the Board of the French National Authority for Health (HAS) regarding the use of the IXCHIQ and VIMKUNYA vaccines in the context of active circulation of the chikungunya virus with a risk of an epidemic developing in the Indian Ocean
- Information on the IXCHIQ vaccine
- Information on the VIMKUNYA vaccine
- Chikungunya Vaccination | vaccination-info-service.fr
- Health Recommendations for Travelers | High Council for Public Health
Community Prevention and Vector Control
Vector control refers to all measures used to combat and protect against mosquitoes that transmit dengue. Strategies depend on the vectors as well as the epidemiological and socioeconomic context. These include chemical control, biological control, genetic control, environmental interventions, health education, and community engagement. Finally, the effectiveness of these methods is subject to ongoing evaluation.
Vector control operations may be initiated by the Regional Health Agency (ARS) when a public health risk is identified. These are targeted, strictly regulated interventions that are part of a public health strategy aimed at reducing the risk of local transmission of diseases such as dengue fever. They aim to minimize the number of adult mosquitoes that may have bitten an infected person and could therefore transmit the disease to others in the vicinity. Along with other public health measures, they also aim to reduce the risk of endemicity (the long-term establishment of a disease in a region) or the occurrence of epidemics, to reduce the transmission of pathogens by vectors, and to manage outbreaks of vector-borne diseases—all within a formalized strategic framework.
Depending on the scale at which this mosquito control is carried out, a distinction is made between control carried out at the regional level (departments, municipalities) and that implemented at the individual level, which specifically targets mosquito breeding sites (larval habitats) located in the immediate vicinity of homes.
Vector control at the regional level is carried out by public mosquito control agencies. Chemical control has two components:
- Larvicides, which specifically target mosquito larvae
- Adulticides, which specifically target adult mosquitoes
Treatment
There is no specific antiviral treatment for chikungunya. Management is therefore primarily symptomatic, aimed at relieving symptoms. Pain and fever are treated with analgesics and antipyretics.
It is important to explain to the patient and their family and friends that mosquito prevention measures can help prevent transmission at home (see “How can individuals prevent the disease?”). During the viremic phase of the illness, the patient must protect themselves from mosquito bites. This prevents new mosquitoes from becoming infected by biting the patient, thereby reducing the risk of spreading the disease to those around them.
A Mosquito Established in Metropolitan France
Aedes albopictus (also known as the tiger mosquito) is considered the most invasive mosquito species in the world. It is native to Southeast Asia, from where it spread through commercial transportation. In Europe, it was first identified in Albania in 1979 and then in Italy in 1990. It has been established in southern France since 2004 and has been gradually spreading since then, particularly in Southern and Central Europe.
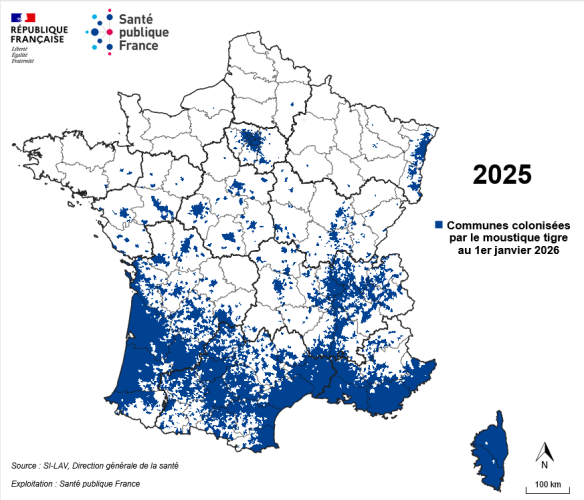
By early 2026, 83 departments were infested with the Aedes albopictus mosquito (out of the 96 departments in mainland France).
Departments in mainland France where the Aedes albopictus vector is present
Municipalities infested with the tiger mosquito as of January 1, 2026
Links
In relation to

Dengue
thematic dossier
Dengue fever is a viral disease transmitted by mosquitoes of the genus Aedes. The most common symptoms are fever and joint pain. Its complications can be severe.

Zika
thematic dossier
Zika is a viral disease transmitted primarily by mosquitoes but also through sexual contact. Symptoms are usually mild, but the virus can cause birth defects if a woman becomes infected during...











